

All claims must be submitted on the most recent approved ABI Claims Submission Form. Each spreadsheet should be completed and include the following:
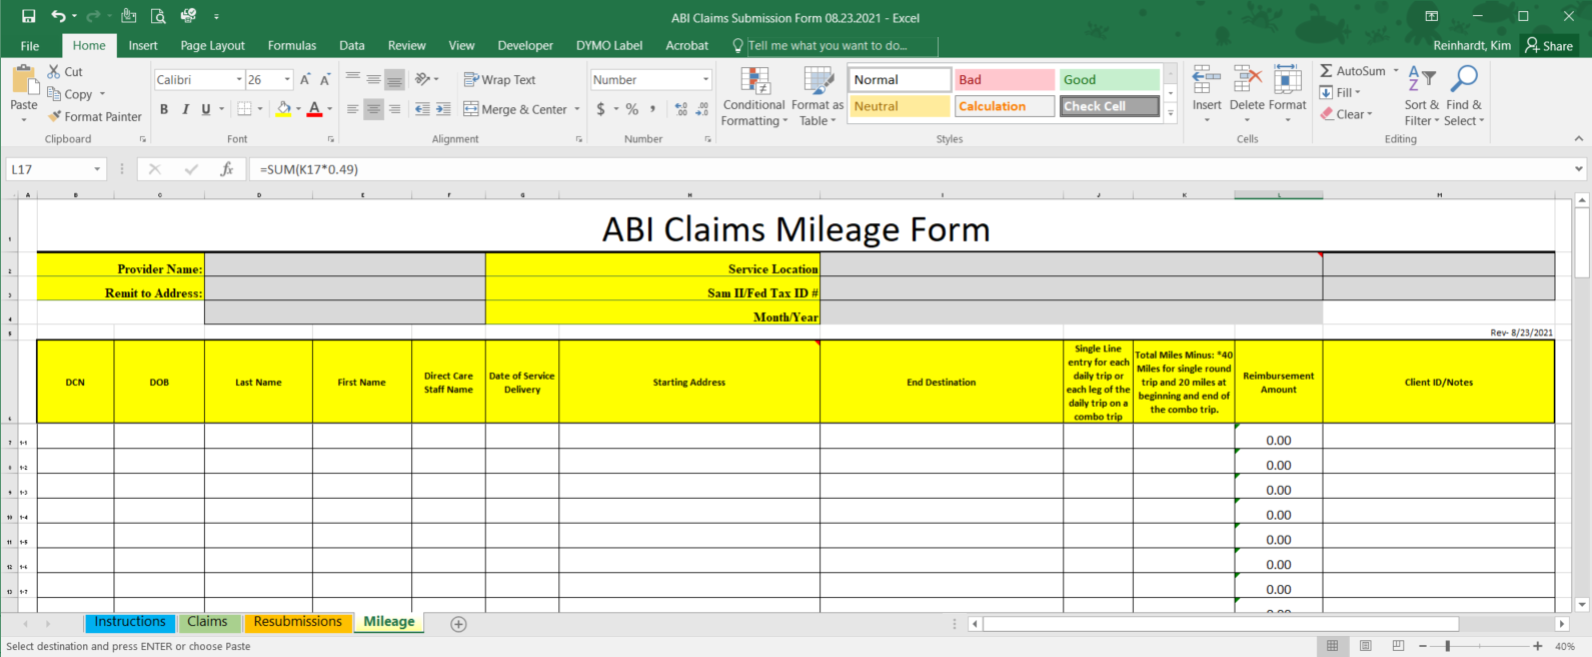
- Cover no more than one (1) month of services for all participants served by the Provider;
- List each participant’s Department Client Number (DCN);
- Indicate the date service was provided;
- Indicate the service code and number of units for the service provided; and
- Email to ABIClaims@health.mo.gov.
NOTE: Consultation visits require a related service code to be entered in the Client ID/Notes column in order to be reimbursed.
Determining Billing Units
- Use the attendance record for the participant for the date of service;
- Add the number of units that most closely approximates the time the participant received the service; and
- Multiply the Reimbursement Rate for the service received by the number of units the participant received on that date. (Contact time-see examples below).
- All billable units must occur face to face with the participant, unless prior approved by ABI Program Manager.
When the time of service exceeds a unit time, the Provider is entitled to bill for the next unit up to the total number of units approved.
- Example 1 (1/4 hour unit): The participant attended the scheduled service for 50 minutes. The participant was prior approved for four (4) units. The billable number of units is four (4) units, since the participant attended for a portion of the fourth unit of the approved time.
- Example 2: The participant attended the scheduled service the entire week, however, missed one entire afternoon for a medical appointment. The participant was prior approved for five (5) full days. The billable number of units is: Five (5) full days. Since there are two different codes for full and half days, even though the participant did not attend for a full day, a half-day unit has not been approved, and will be rejected.
Mileage Reimbursement
Mileage shall be reimbursed to ABI Providers at the State of Missouri’s current standard mileage reimbursement rate. ABI Providers will be reimbursed for services delivered outside of a 20-mile radius of the direct care staff worker delivering services or the ABI Provider’s local office, whichever is closer. An ABI Provider can only bill up to a total of 150 miles for a round trip per participant, per visit.
The current standard mileage reimbursement rate is subject to change at any time.
- The direct care staff worker must be outside of a 20-mile radius (one-way) to the participant receiving services.
- If the Provider agency’s local office (closest office to the participant) is within a 20-mile radius (one-way) of the participant receiving services, mileage will not be reimbursed.
- Mileage will not be reimbursed while the direct care staff worker is delivering services to the participant.
- Trips that are 40 miles or less (round trip) should not be submitted.
- Mileage reimbursement submissions must include the entire trip (including the 20 miles). If multiple visits are conducted within the same trip, separate line entry is required for each participant.
- Acceptable supporting documents can be requested at any time and should be made available upon request. Examples of acceptable supporting documents are as follows:
- Google map printout along with a picture of the odometer reading at the time-of-service delivery.
- Map Quest printout along with a picture of the odometer reading at the time-of-service delivery.
- Tracking log approved/submitted by the direct care staff and approved by the direct care staff supervisor.
- Details of the mileage reimbursement request must be entered on the ABI Claims Submission Form on the Mileage tab.
- If mileage is submitted for a participant receiving services but the participant is not included on the Claims tab for services, the provider must include an explanation for the mileage in the Notes column on the Mileage tab in order to be reimbursed.
- Examples of mileage scenarios for reimbursement can be found within the ABI Claims Submission Form on the Instructions tab.
Submitting the ABI Claims Submission Form
The ABI Claims Submission Form should be submitted to: ABIClaims@health.mo.gov.
All billings for approved services provided to approved participants must be submitted to the Department no later than sixty (60) days following the date services are provided. At the close of a state fiscal year, Providers shall be notified by the ABI Program to submit the ABI Claims Submission Form at an earlier date to ensure timely payment.
The ABI Program will not provide co-payment for services covered under any other program (MO HealthNet, Medicare, or private insurance).
When participants are covered by third-party payers that also cover the billed service, approval can be considered for payment only if a written denial has been submitted with each request for approval of services (Prior Authorization Form).
ABI claims will be reimbursed at established rates outlined in the Provider Manual and as prior authorized. When the claim has been processed, a voucher will be sent at the time of payment to the address listed during Provider enrollment. Payment is typically issued 30-45 days from receipt of the ABI Claims Submission Form.
If a claim is denied for any reason, an explanation will be printed on the voucher. Typical reasons for denial may include:
- Service not prior authorized;
- Claim not filed within 60-day timeline; or
- Adjusted to prior authorization
Resubmissions
If claims staff identify a billing issue for a specific participant that cannot be resolved immediately, a notification will be sent to the Provider requesting a resubmission. The Provider will make the needed corrections on the Resubmissions tab of the most recent ABI Claims Submission Form and submit to ABIClaims@health.mo.gov.
Credit/Recoupments
Credits/recoupments will be processed in the following circumstances:
- Duplicate payments;
- Insurance payments;
- MO HealthNet payments;
- Payments made in error; or
- Overpayments
The credit/recoupment will be reflected on the next payment and voucher processed to the Provider. Refunds should not be sent unless requested from the Department of Health and Senior Services (DHSS).
Correspondence
Any correspondence or payment sent by the DHSS will be sent to the address shown on the Provider Participation Agreement. It is the responsibility of the Provider to notify SHCN if the contact person, address or county coverage changes. Organizational charts or employee listing should be provided to the ABI Program Manager upon request.
Monitoring
Providers must maintain accurate participant claims files. DHSS has the authority to review participant records and Provider billings. Program Staff will monitor all providers periodically.
Provider Appeal Process
Special Health Care Needs (SHCN) enrolled providers have the right to appeal decisions regarding denial of payment for services.
To appeal a decision made by SHCN, the provider must submit the following documentation to the Program Manager within thirty (30) calendar days of the SHCN warrant/voucher date:
- A letter describing the reason for the appeal;
- Documentation to support overturning the denial; and
- A copy of the claim being appealed
The Program Manager will review the documentation and render a written decision to the provider within thirty (30) business days of the receipt of the appeal. If the decision is unsatisfactory, the provider may submit a second appeal letter addressed to the Bureau Chief.
The appeal and supporting documentation must be received by SHCN within thirty (30) calendar days of the Program Manager’s written decision date. The Bureau Chief will review the documentation and render a written decision to the provider within thirty (30) business days of the receipt of the appeal.
If the decision is unsatisfactory, the provider may submit a final appeal letter to the Department Director, or designee. The appeal and supporting documentation must be received by SHCN within thirty (30) calendar days of the Bureau Chief’s written decision date. The Department Director will make a final decision based on the evidence and documentation submitted with the appeal. A letter outlining the Director’s decision will be mailed to the provider within thirty (30) business days of the receipt of the appeal.