
Introduction – Adult Brain Injury Program
Adult Brain Injury Program Provider Manual
Introduction – Adult Brain Injury Program
Purpose
The ABI Program provides assistance in locating, coordinating, and purchasing rehabilitation and psychological services for individuals who are twenty-one (21) to sixty five (65) years of age, and who are living with a traumatic brain injury (TBI). RSMo Section 192.735 defines a TBI as “a sudden insult or damage to the brain or its coverings, not of a degenerative nature. Such insult or damage may produce an altered state of consciousness and may result in a decrease of one (1) or more of the following: mental, cognitive, behavioral, or physical functioning resulting in partial or total disability. Cerebral vascular accidents, aneurysms, and congenital deficits are specifically excluded from this definition.”
The ABI Program provides two primary services: service coordination and rehabilitation services.
Service Coordination includes:
- Evaluation and assessment of needs
- Development, regular evaluation and updates of a treatment plan (applies to rehabilitation services only)
- Assistance in locating and accessing resources such as medical care, housing, counseling, transportation, rehabilitation, vocational training, and cognitive/behavior training
- Information, education, and advocacy (applies to rehabilitation services only) Service Coordination is provided to all ABI Program participants, regardless of financial status.
Rehabilitation Services
Are provided to participants who meet financial guidelines and when it has been determined, the services are necessary to facilitate a long-term goal as indicated in the ABI Treatment Plan. ABI Treatment Rehabilitation services as listed in this manual are available to individuals who are medically eligible and whose income is 185% of Federal Poverty Guidelines or lower. Certain limitations apply and this manual outlines operational procedures for use of Department of Health and Senior Services (DHSS) ABI funds.
Rehabilitation services include:
- Neuropsychological Evaluation and Consultation
- Adjustment Counseling
- Transitional Home and Community Support Training
- Pre-vocational/Pre-employment Training
- Supported Employment/Follow Along
- Special Instruction
- Consultation Visit
The ABI Service Coordinator will assist the participant to apply for any other payment resources before submitting requests for use of ABI funds to purchase these services, since it is a requirement that the participant utilize other resources first.
- When DHSS funds are used to purchase services, costs of the proposed rehabilitation services will be projected;
- Services will be initiated only when adequate funds are available to achieve an expected outcome goal; and
- When the demand for services exceeds available funds, the ABI Program will implement a waiting list for services.
History
The ABI Program was created in 1985 when the Missouri General Assembly appropriated $500,000 for community services for individuals with TBI and their families. Funds are appropriated annually by the legislature.
DHSS put into place two ABI Service Coordinators dedicated to the ABI Program in 1994. This allowed the beginnings of a case management service delivery system. In FY99, statewide coverage became a reality with a service coordination team of eight (8) specialized ABI Service Coordinators. There are currently eleven (11) ABI Service Coordinators located throughout Missouri.
Service Delivery Model
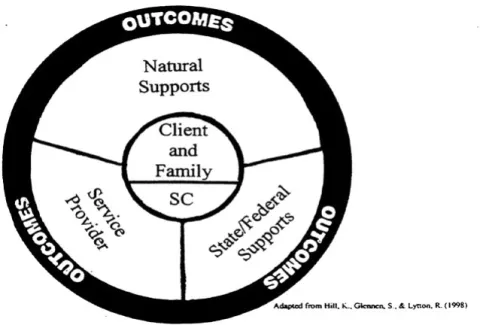
The ABI Program is neither an entitlement program nor an entitlement to lifelong care and treatment. The ABI Program utilizes a person-centered approach that palces the ABI Service Coordinator with the participant and family at the center of the assessment, planning, and service delivery efforts for each individual. Just-in-time, rehabilitative services shall be scheduled around the participant/family’s goals and resources thereby enhancing the individual’s opportunity to achieve a successful outcome of community integration and productive lifestyle.
Role/Responsibility of the ABI Service Coordinator
The ABI Service Coordinator is the entry point into ABI Program. Upon referral, each participant is assigned an ABI Service Coordinator, based on the individual’s county of residence. The ABI Service Coordinator assesses the participant’s immediate needs and assists the individual to access resources that may be available, such as public programs or natural supports.
The ABI Service Coordinator, together with the individual, family, and provider develops a Treatment Plan. The Treatment Plan outlines a long-term projected outcome goal, such as return to work or independent living, and the steps to achieve this goal. These steps may include referral for any public programs, development of skills through rehabilitative services or development of other supports that will assist the individual to reach the maximal level of independent community functioning. Together the ABI Service Coordinator and the family identify key people to form the Person-Centered Planning Team. The planning team that works with the individual should always include: the participant, the ABI Service Coordinator, Provider Agency, involved family member(s), significant other(s), and/or the legal guardian. Other members will be added at appropriate times given changing needs as the participant moves through services toward functional independence. The ABI Service Coordinator actively assures the ongoing coordination and functioning of the planning team. The ABI Service Coordinator assures that at least a bi-annual review of the Treatment Plan is scheduled. The ABI Service Coordinator also assures that a transition plan is in place when unmet needs continue beyond the scope of the ABI Program.
Provider Enrollment and Role/Responsibility
The Provider must meet certain qualifications to be enrolled with Special Health Care Needs (SHCN) to provide ABI Program rehabilitative services. These qualifications and the process for enrollment are listed elsewhere in this manual. The Provider is an active member of the planning team while involved with an individual, and as such is expected to collaborate with the entire team. Collaboration across programs and services is a key component of the person-centered service delivery model, and requires effective and timely communication between all agencies and participants involved.
Purpose of the Provider Manual
The Provider Manual outlines operational guidelines for participating in the ABI Program, and use of DHSS funds for rehabilitative services. The manual is divided into the following sections:
- Introduction;
- Services Mission, Philosophy and Values;
- General Program Guidelines;
- Program Entry Procedures;
- Rehabilitation Services Available;
- Billing/Claims Procedures;
- Provider Enrollment Procedures; and
- Appendices.
The Provider Manual is reviewed for changes by DHSS staff. Providers will be notified of any revisions to the Provider manual. The Provider Manual is available on the ABI Program Provider website.
Communication
Communication from DHSS may occur through a variety of methods. To assure that the Provider receives communications in a timely manner, the Provider should identify a contact person to receive program-related information. The Provider should specify if the contact person is at a different location than the main address/billing location. Examples of the types of expected communications are listed below:
- Regular Mail: Implementation of a waiting list; copy of response to Prior Authorization request; significant procedural changes, that affect all providers;
- Phone or email: Specific participant questions/concerns or procedural questions (DHSS encryption required to be utilized for Protected Health Information (PHI) correspondence);
- Fax: Early responses to Prior Authorization requests (see Prior Authorization Procedures); and General Program informational updates.